
Quick Medical Summary: The human liver (hepar) executes over 500 vital metabolic functions, processing 1.4 liters of blood per minute. True hepatic biotransformation is not achieved through fad juice cleanses, but via an exact three-phase biochemical cascade: Phase I oxidation (CYP450 enzymes), Phase II conjugation (requiring sulfur amino acids and glutathione), and Phase III canalicular bile excretion. Clinically validated hepatoprotective botanicals—particularly phospholipid-bound silymarin (milk thistle), choleretic globe artichoke, and glutathione-precursor N-Acetyl Cysteine (NAC)—accelerate hepatocyte regeneration and protect against metabolic fatty liver (MASLD). Seek urgent medical care for jaundice (yellowing skin/eyes), right upper quadrant abdominal swelling, or dark urine with pale stools.
Weighing approximately three pounds and performing more than 500 distinct vital physiological functions, the human liver (hepar) is the body’s ultimate metabolic factory, chemical processing plant, and immunological filter. Every minute, roughly 1.4 liters of blood circulates through hepatocytes and resident Kupffer macrophages via the portal vein and hepatic artery, dismantling wastes, neutralizing xenobiotics, and regulating systemic metabolism.
In modern society, ultra-processed foods, liquid fructose, pesticides, and pharmaceuticals have driven Metabolic Dysfunction-Associated Steatotic Liver Disease (MASLD) into an epidemic affecting over 30% of adults worldwide.
Contrary to unscientific juice cleanses, hepatic detoxification is an enzymatically complex biochemical process requiring micronutrient cofactors, amino acids, and evidence-based botanical bioactives. Below is a clinical guide to hepatic clearance, premier hepatoprotective herbs, and liver longevity.
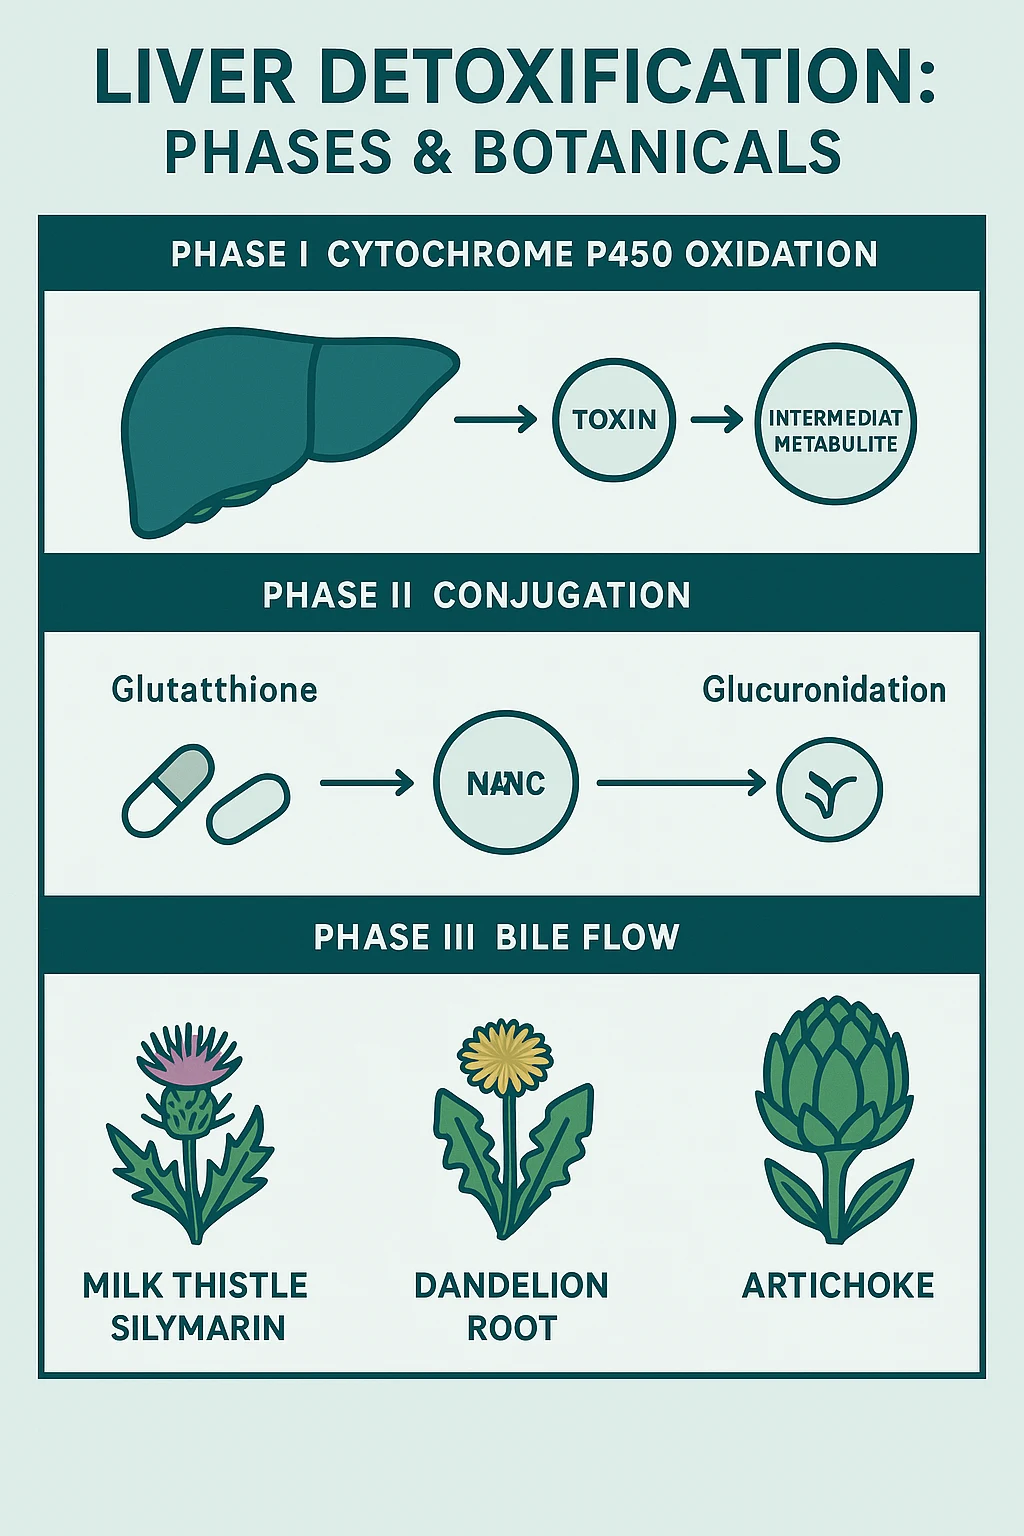
1. The Tri-Phasic Detoxification Architecture: How the Liver Actually Cleanses
Hepatic biotransformation does not occur in a single step. Fat-soluble (lipophilic) compounds—including fat-soluble pesticides, industrial plasticizers, heavy metals, steroid hormones, and pharmaceutical metabolites—are inherently resistant to excretion via watery bile or urine. To safely eliminate them, hepatocytes execute an interconnected three-phase biochemical cascade:
Phase I: Functionalization (The Cytochrome P450 Superfamily)
Located primarily within the smooth endoplasmic reticulum of hepatocytes, the Cytochrome P450 (CYP450) heme-containing enzyme superfamily carries out Phase I biotransformation. Through oxidation, reduction, and hydrolysis reactions, CYP enzymes (such as CYP1A2, CYP2E1, and CYP3A4) introduce or unmask a polar reactive functional group (such as a hydroxyl $-OH$, carboxyl $-COOH$, or amino $-NH₂$ group) onto the lipophilic toxin molecule.
The Phase I Toxic Hazard: Crucially, these newly created Phase I intermediate metabolites are frequently far more reactive, mutagenic, and chemically unstable than the parent compounds. If not rapidly captured and neutralized by Phase II conjugation, these reactive oxygen species (ROS) and free-radical intermediates trigger lipid peroxidation of hepatocyte cell membranes, deplete intracellular glutathione, and cause localized hepatic inflammation.
Phase II: Conjugation (The Molecular Neutralization Pathways)
In Phase II, hepatocytes attach a large, water-soluble endogenous molecule directly onto the reactive functional site of the Phase I intermediate, rendering it completely inert, non-toxic, and ready for excretion. Phase II operates through six specialized enzymatic pathways, each requiring specific nutritional substrates:
- Glutathione Conjugation (GST): Primary defense against heavy metals, pesticides, and reactive metabolites, dependent on intracellular glutathione.
- Sulfation (SULT): Neutralizes steroid hormones, excess estrogens, and xenobiotics using bioavailable dietary sulfur from allium and cruciferous vegetables.
- Glucuronidation (UGT): High-capacity pathway clearing bilirubin, NSAIDs, statins, and plasticizers via glucuronic acid.
- Methylation (COMT): Inactivates catechols, neurotransmitters, and estrogen metabolites, requiring SAMe, Vitamin B12, and active folate.
- Amino Acid Conjugation: Binds food preservatives and aromatic acids with glycine or taurine to form excretable hippuric acid.
- Acetylation (NAT): Detoxifies histamines, tobacco carcinogens, and environmental toxins via acetyl-CoA and Vitamin B5.
The Dangerous “Phase I / Phase II Pathological Mismatch”
A frequent clinical scenario observed in functional hepatology is a severe enzymatic imbalance: hyperactive Phase I clearance paired with sluggish, depleted Phase II conjugation. When excessive alcohol, medications, or pollutants induce CYP450 enzymes without sufficient Phase II amino acid substrates (cysteine, glycine, methionine), reactive intermediates back up in hepatic tissue. Our clinical guide to alcohol use disorder and liver recovery details how this mismatch damages mitochondrial membranes. This pathological bottleneck is a primary biochemical driver of chronic chemical sensitivity, unexplained fatigue, skin eruptions, and progressive steatohepatitis.
Phase III: Cellular Transport & Canalicular Bile Flow
Once neutralized, Phase II water-soluble conjugates must be actively pumped out of hepatocytes into either the bloodstream (for filtration by the kidneys into urine) or across the canalicular membrane into bile. This transport is orchestrated by ATP-binding cassette (ABC) transporters, including P-glycoprotein and the bile salt export pump (BSEP). Once inside the biliary tree, toxins are swept through the gallbladder into the duodenum and eliminated via bowel movements—highlighting why preventing sluggish motility with evidence-based natural remedies for constipation and supporting healthy gut microbiome balance is mandatory to stop conjugated toxins from reabsorbing into enterohepatic circulation.
2. Evidence-Based Hepatoprotective Botanicals: Active Bioactives & Mechanisms
While generic commercial “liver detox teas” rely on harsh laxatives (like senna), authentic herbal hepatoprotection is defined by specific phytochemicals that stabilize hepatocyte membranes, upregulate endogenous antioxidant enzymes, and stimulate physiological bile production:
1. Milk Thistle (Silybum marianum) & The Silymarin Complex
As evaluated in a comprehensive clinical review on milk thistle in liver diseases (PMID: 28710148), Milk Thistle is the gold standard botanical in clinical hepatology. Its therapeutic efficacy is concentrated in Silymarin, a standardized mixture of flavonolignans comprising silybin (silibinin) A and B, isosilybin A and B, silychristin, and silydianin.
Silymarin operates through four distinct molecular mechanisms:
- Ribosomal Protein Synthesis: Silybin stimulates nucleolar RNA polymerase I, accelerating ribosomal RNA transcription and structural protein synthesis to promote hepatocyte regeneration.
- Membrane Stabilization: Alters hepatocyte outer membrane architecture and receptor permeability, physically blocking xenobiotics and fungal toxins from entering cells.
- Antioxidant Upregulation: Scavenges free radicals, inhibits mitochondrial lipid peroxidation, and elevates intracellular glutathione (GSH) and superoxide dismutase (SOD) by up to 35%.
- Anti-Fibrotic Action: Suppresses the phenotypic activation of hepatic stellate cells into collagen-depositing myofibroblasts, attenuating fibrotic progression.
Clinical Bioavailability Note: Standard powdered silymarin exhibits poor oral bioavailability (approx. 20% to 50%) due to low water solubility. Advanced formulations utilizing Siliphos® (Silybin Phytosome)—where silybin is molecularly bound to soy or sunflower phosphatidylcholine—yield nearly 5 times higher active absorption into human systemic and hepatic circulation.
2. Globe Artichoke (Cynara scolymus) & Cynarin
Globe artichoke leaves contain high concentrations of caffeoylquinic acids (chiefly cynarin and chlorogenic acid) and bioflavonoids such as luteolin. Artichoke extract acts as a potent choleretic (stimulating hepatocytes to synthesize and secrete fresh bile acids) and cholagogue (triggering gallbladder contraction to discharge stored bile into the intestinal lumen).
By increasing bile secretion, artichoke accelerates Phase III toxin excretion, discourages biliary sludge, and supports healthy cholesterol metabolism. In a landmark randomized double-blind clinical trial on artichoke leaf extract in NAFLD (PMID: 29520889), artichoke extract significantly reduced serum liver transaminases (ALT, AST) while improving portal vein blood flow.
3. Dandelion Root (Taraxacum officinale) & Hepatic Bitters
Often dismissed as an invasive lawn weed, the science explored in our clinical guide on dandelion root healing benefits shows it is a classic hepatobiliary tonic in herbal pharmacopoeias. Rich in sesquiterpene lactones (taraxacin), triterpenes (taraxasterol), and inulin (a prebiotic soluble fiber), dandelion root activates bitter taste receptors on the tongue and throughout the upper digestive tract.
This bitter stimulus triggers vagal reflexes that promote bile secretion. Pharmacological studies confirm dandelion polysaccharides protect hepatocytes from oxidative stress by upregulating the Nrf2 antioxidant pathway.
4. N-Acetyl Cysteine (NAC) & Glutathione Biosynthesis
N-Acetyl Cysteine (NAC) is the acetylated precursor to L-cysteine, the rate-limiting amino acid required for cellular synthesis of Glutathione (GSH)—the “master antioxidant” of the human body. In emergency medicine, intravenous NAC is the standard-of-care hospital antidote administered to reverse acute liver failure caused by acetaminophen toxicity.
Daily oral NAC (600–1,200 mg) replenishes intracellular glutathione, curbs mitochondrial oxidative stress, and provides sulfur donors for Phase II sulfation.
3. Metabolic Fatty Liver (MASLD): The Two-Hit Pathological Mechanism
Non-alcoholic fatty liver disease (MASLD) has surpassed viral hepatitis as the leading cause of chronic liver disease in developed nations. Its pathogenesis is defined by the widely accepted “Two-Hit Hypothesis”:
- First Hit (De Novo Lipogenesis): Excessive liquid fructose and refined sugars overwhelm hepatic metabolism, fueling unchecked intrahepatic triglyceride accumulation (steatosis).
- Second Hit (Oxidative Stress & Inflammation): Lipid overload triggers mitochondrial beta-oxidation failure and reactive oxygen leakage, activating NF-κB and advancing steatosis to steatohepatitis (MASH) and fibrosis.
4. The Clinical Diagnostic Liver Panel: How to Interpret Your Bloodwork
Evaluating liver health requires analyzing a comprehensive hepatic panel rather than relying on a single isolated enzyme. Below is the clinical interpretation matrix:
| Enzyme / Biomarker | Standard Clinical Range | Optimal Functional Target | Clinical Significance |
|---|---|---|---|
| Alanine Aminotransferase (ALT) | 7 – 56 U/L | 12 – 25 U/L | Liver-Specific Enzyme: Found in hepatocyte cytoplasm. Spills into blood upon membrane damage; levels > 30 U/L correlate with early steatosis. |
| Aspartate Aminotransferase (AST) | 10 – 40 U/L | 15 – 25 U/L | Present in liver and muscle. De Ritis Ratio (AST/ALT): < 1.0 indicates steatosis/MASLD; > 2.0 suggests alcoholic injury or advanced fibrosis. |
| Gamma-Glutamyl Transferase (GGT) | 9 – 48 U/L | 10 – 22 U/L | Early Marker of Biliary Stasis & Oxidative Stress: Catalyzes glutathione degradation. Highly elevated in alcohol use and biliary congestion. |
| Alkaline Phosphatase (ALP) | 44 – 147 U/L | 50 – 85 U/L | Originates from bile duct epithelium and bone. Elevations paired with elevated GGT confirm biliary duct obstruction or cholestasis. |
| Ferritin (Iron Storage) | 30 – 400 ng/mL (Men) 15 – 150 ng/mL (Women) | 50 – 100 ng/mL | Acute-phase reactant. Significant elevations reflect active hepatic necroinflammation and oxidative iron storage. |
5. Step-by-Step Liver Longevity & Regeneration Protocol
To support your liver’s innate capacity for self-repair and keep all three detoxification phases operating in harmony, implement this structured four-tier protocol:
- Eradicate Liquid Fructose & Excess Alcohol: Eliminate sodas, commercial juices, and high-fructose corn syrup to halt de novo lipogenesis at the source and give hepatocytes dedicated time to clear stored lipids.
- Incorporate Phase II Sulfur & Cruciferous Glucosinolates: Eat two daily cups of cruciferous vegetables (broccoli sprouts, kale) rich in sulforaphane-inducing glucosinolates, alongside sulfur-rich alliums (garlic, onions) to fuel glutathione synthesis.
- Use Digestive Bitters & Choleretics: Drink roasted dandelion root tea or take globe artichoke extract before meals to stimulate bile acid production and promote Phase III excretion.
- Deploy Targeted Hepatoprotective Botanicals: Utilize clinically bioavailable Siliphos® Milk Thistle Phytosome paired with N-Acetyl Cysteine (NAC) for dual-action hepatocyte regeneration and antioxidant replenishment.
Recommended Hepatoprotective Supplements
Third-party certified, clinically bioavailable botanicals selected by our editorial team.
Thorne Siliphos (Milk Thistle Phospholipid Complex)
Features patented Siliphos® technology binding silybin to sunflower phospholipids, providing 5x greater cellular absorption than standard milk thistle powders to support hepatocyte regeneration.
Pure Encapsulations NAC 600mg (N-Acetyl-L-Cysteine)
Pharmaceutical-grade, hypoallergenic N-Acetyl Cysteine providing the critical rate-limiting amino acid for Phase II glutathione conjugation and cellular liver defense.
Traditional Medicinals Organic Roasted Dandelion Root Tea
Pharmacopoeial-grade organic roasted dandelion root stimulating bitter taste receptors, supporting healthy bile secretion and Phase III gastrointestinal toxin elimination.
A major driver of hepatic toxic load is dietary pesticide contamination; read the investigative analysis on glyphosate levels found in popular food brands to protect liver function.
Related Clinical & Digestive Guides
- Herbal Biliary Support: Dandelion Healing Benefits: Liver Detox, Inulin Science & Bile Flow
- Bowel Motility & Toxin Clearance: Natural Remedies for Constipation: 7 Proven Ways to Restore Regularity
- Microbiome Barrier Defense: The Complexity of the Gut: Microbiome, Mucosal Immunity & Digestion
- Alcohol & Hepatic Repair: Alcohol Use Disorder: Safe Detox Protocol & Cellular Liver Recovery
- Metabolic Digestive Health: Apple Cider Vinegar: 7 Science-Backed Uses for Health & Metabolism
Frequently Asked Questions (FAQ)
Do commercial 3-day juice cleanses actually detoxify the liver?
No. Fasting on high-sugar commercial fruit juices is physiologically counterproductive. Phase II enzymatic conjugation requires continuous supplies of amino acids (glycine, cysteine, taurine, methionine) and sulfur. A low-protein juice fast starves Phase II pathways while flooding the liver with liquid fructose, which accelerates de novo lipogenesis. Real hepatic support requires adequate dietary protein, sulfur-dense vegetables, and targeted botanicals rather than calorie deprivation.
How long does it take for fatty liver to reverse?
Because hepatocytes possess extraordinary regenerative capacity, early-stage non-alcoholic hepatic steatosis begins reversing rapidly. Clinical imaging trials demonstrate that eliminating liquid fructose and alcohol, combined with daily aerobic movement and silymarin supplementation, produces a statistically significant reduction in intrahepatic lipid volume within 4 to 8 weeks, with normalized ALT and AST transaminases typically observed within 3 to 6 months.
Can you take Milk Thistle alongside prescription medications?
Generally yes, but caution is warranted with certain drug classes. Because silymarin mildly modulates Cytochrome P450 3A4 (CYP3A4) and 2C9 enzymes as well as P-glycoprotein efflux pumps, it can theoretically alter the serum clearance of narrow therapeutic index drugs (such as warfarin, certain anti-epileptics, and immunosuppressants). Patients taking prescription medications should consult their prescribing physician before initiating high-dose silymarin phytosome therapy.
Final Medical Verdict
The human liver does not require faddish gimmicks to maintain optimal function—it is already equipped with nature’s most sophisticated bio-filtration machinery. By providing the essential sulfur and amino acid building blocks for Phase II conjugation, promoting unimpeded Phase III bile flow with herbal bitters, and protecting hepatocyte cell membranes with clinically bioavailable silymarin and NAC, you grant your liver the exact biochemical tools it requires to thrive and protect your systemic health for a lifetime.