
Quick Medical Summary: Irritable Bowel Syndrome (IBS) is a disorder of gut-brain interaction (DGBI) defined by the Rome IV diagnostic criteria as recurrent abdominal pain linked to defecation or changes in stool frequency and form. Rather than being a psychosomatic complaint, IBS is driven by quantifiable molecular pathologies: visceral hypersensitivity, dysregulated serotonin (5-HT) signaling, low-grade mucosal immune activation, and small intestinal bacterial overgrowth (SIBO). First-line therapies include the 3-phase Monash Low-FODMAP diet, gut-directed relaxation, and targeted botanicals—notably enteric-coated peppermint oil (L-menthol, a smooth muscle L-type calcium channel blocker) and prebiotic partially hydrolyzed guar gum (PHGG). Immediate medical evaluation is required for alarm symptoms: nocturnal diarrhea, unexplained weight loss, rectal bleeding, or onset after age 50.
Affecting an estimated 10% to 15% of adults globally, Irritable Bowel Syndrome (IBS) is one of the most prevalent functional gastrointestinal disorders encountered in clinical medicine. Historically, patients were dismissed with vague assurances that their symptoms were “purely stress-related.” Modern neuro-gastroenterology has dismantled this paradigm, revealing IBS as a complex Disorder of Gut-Brain Interaction (DGBI) rooted in quantifiable neurochemical and microbial pathologies.
Furthermore, up to 78% of IBS patients exhibit Small Intestinal Bacterial Overgrowth (SIBO), while others suffer from post-infectious mucosal hyperpermeability. Below is an evidence-based clinical guide to the Rome IV diagnostic criteria, neuro-microbial mechanisms, the 3-phase Low-FODMAP protocol, and targeted botanical therapeutics.
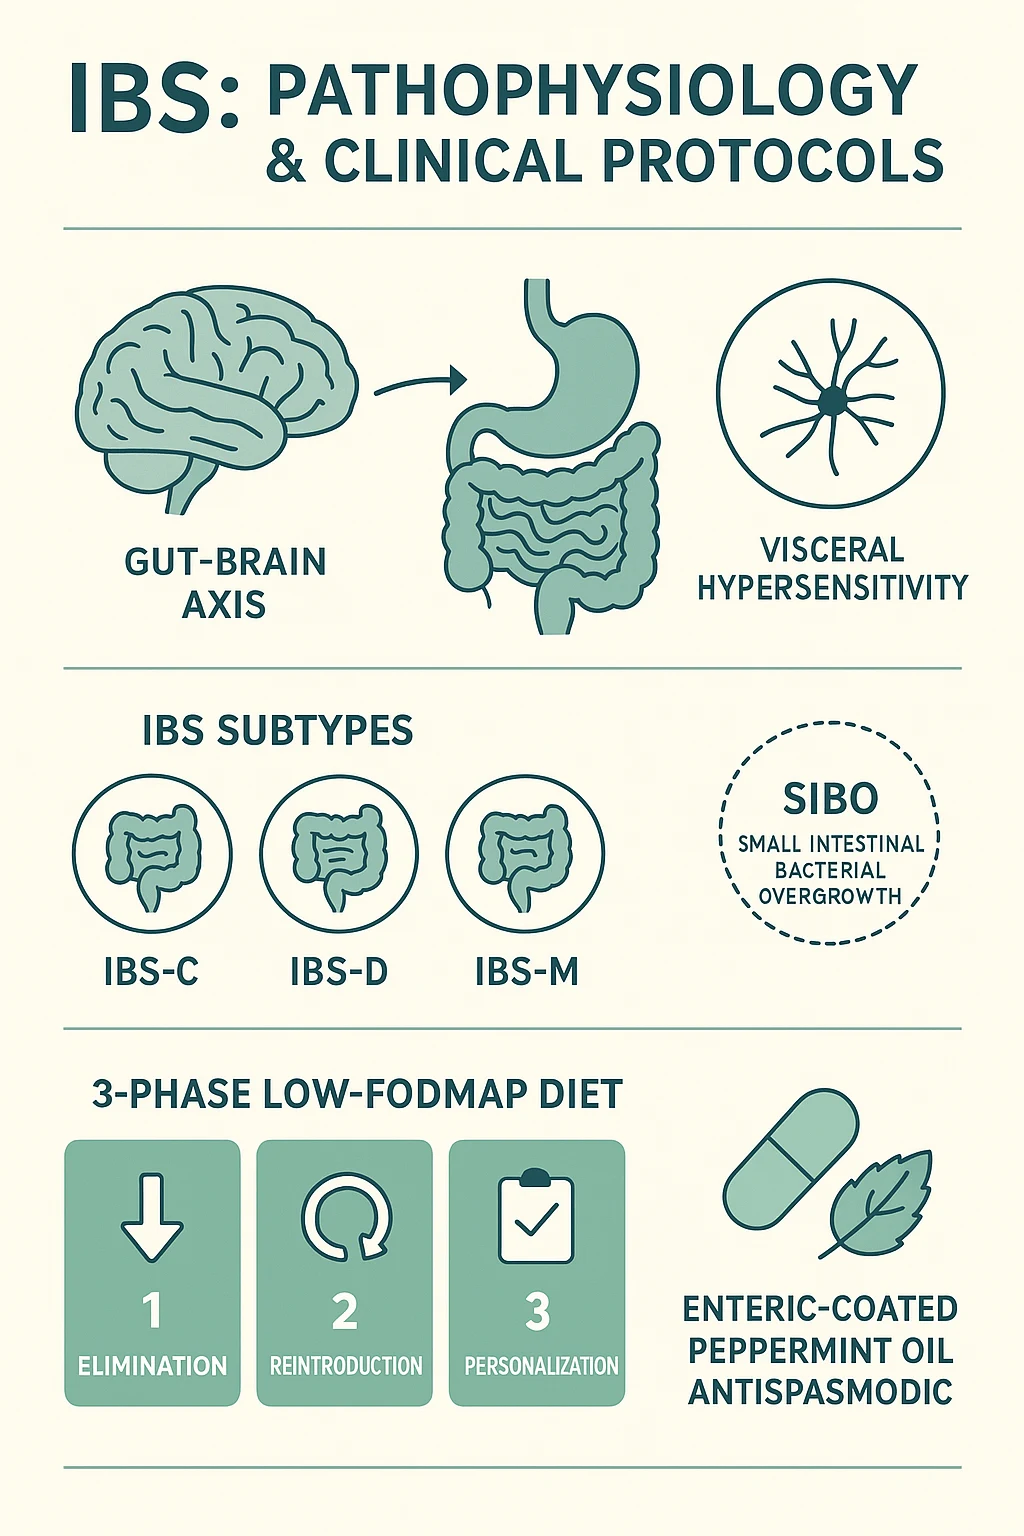
1. Rome IV Diagnostic Criteria & The 4 Clinical Phenotypes
Because IBS does not present with macroscopic structural lesions on conventional imaging, clinical diagnosis is standardized globally using the Rome IV Diagnostic Consensus Criteria. Under Rome IV, an official diagnosis of IBS requires:
Rome IV Diagnostic Criteria: Recurrent abdominal pain occurring on average at least 1 day per week in the last 3 months, associated with two or more of the following: (1) related to defecation, (2) associated with a change in stool frequency, and (3) associated with a change in stool form (appearance).
As emphasized in the American College of Gastroenterology (ACG) Clinical Guideline on IBS Management (PMID: 33315623), applying strict Rome IV parameters alongside routine screening for celiac disease and fecal calprotectin prevents unnecessary invasive colonoscopies in young patients without alarm features.
The Bristol Stool Form Subclassification
To tailor therapeutic protocols accurately, gastroenterologists categorize IBS into four distinct phenotypes based on the patient’s predominant stool consistency on days with abnormal bowel movements, utilizing the validated Bristol Stool Form Scale (BSFS):
- IBS-C (Constipation-Predominant): Over 25% of bowel movements are hard, lumpy pellets (Bristol Type 1–2), while fewer than 25% are loose or watery. Management focuses on restoring colonic hydration and smooth motility, as detailed in our guide on natural remedies for constipation.
- IBS-D (Diarrhea-Predominant): Over 25% of bowel movements are mushy or watery (Bristol Type 6–7), with fewer than 25% hard or lumpy. Characterized by rapid transit and bile acid malabsorption.
- IBS-M (Mixed Bowel Habits): Over 25% of bowel movements are hard and lumpy, and over 25% are loose and watery. Patients alternate unpredictably between constipation and diarrhea.
- IBS-U (Unclassified): Diagnostic criteria for IBS are met, but bowel habits cannot be accurately categorized into the three primary subtypes.
2. The 4 Underlying Molecular Mechanisms of IBS
Modern functional medicine recognizes that IBS is not a single disease, but a clinical syndrome resulting from overlapping physiological disturbances:
1. The Dysregulated Brain-Gut-Microbiome Axis
The human gastrointestinal tract is innervated by the Enteric Nervous System (ENS)—containing more than 500 million neurons, earning it the moniker “the second brain.” The ENS communicates bidirectionally with the Central Nervous System (CNS) via the vagus nerve, sympathetic prevertebral ganglia, and the hypothalamic-pituitary-adrenal (HPA) axis.
In IBS patients, neuroimaging reveals altered processing within the limbic emotional motor system (anterior cingulate cortex and insula). Chronic psychological stress elevates corticotropin-releasing hormone (CRH), which directly destabilizes intestinal motility, increases mucosal permeability, and stimulates colonic mast cell degranulation.
2. Visceral Hypersensitivity (Central & Peripheral Sensitization)
A hallmark pathophysiological trait of IBS is visceral hypersensitivity. In healthy individuals, the physiologic generation of normal intestinal gas (approx. 200 to 600 mL daily) produces slight mechanical distension that is processed unconsciously by the autonomic nervous system without pain. In IBS patients, sensory afferent C-fibers and spinal dorsal horn nociceptors are chronically sensitized. Normal amounts of gas produce excruciating, stabbing sensations of bloating and cramping—a condition termed allodynia of the gut.
3. Serotonin (5-HT) Signaling Alterations
Approximately 90% to 95% of the human body’s total serotonin (5-hydroxytryptamine, 5-HT) is synthesized not in the brain, but inside specialized enterochromaffin (EC) cells lining the intestinal mucosa. Serotonin acts as the master conductor of gastrointestinal peristalsis, fluid secretion, and sensory transmission:
- In IBS-D: Enterochromaffin cells demonstrate hyper-secretion of serotonin or downregulated serotonin reuptake transporter (SERT) proteins. Elevated extracellular 5-HT overstimulates 5-HT₃ and 5-HT₄ receptors, triggering hyper-motility, rapid colonic transit, and watery secretions.
- In IBS-C: Enterochromaffin cells exhibit blunted serotonin release or impaired 5-HT receptor sensitivity, leading to colonic inertia and severe delayed transit.
4. Low-Grade Mucosal Inflammation & Mast Cell Activation
A substantial subset of cases originate as Post-Infectious IBS (PI-IBS), developing immediately after an acute episode of bacterial gastroenteritis (such as Campylobacter jejuni, Salmonella, or Shigella). In these individuals, intestinal biopsies demonstrate persistent micro-inflammation: elevated infiltration of mast cells and intraepithelial lymphocytes positioned in direct microscopic proximity to enteric nerve fibers. Degranulating mast cells release histamine, tryptase, and prostaglandin E2, which degrade tight junction proteins (zonula occludens-1) and continuously fire neighboring pain receptors.
3. The SIBO Overlap: Is Your IBS Actually a Bacterial Overgrowth?
One of the most transformative breakthroughs in gastroenterology is the discovery of Small Intestinal Bacterial Overgrowth (SIBO). In a healthy human, the vast majority of our 38 trillion gut microbes reside within the large intestine (colon), where bacterial densities reach $10^{11}$ to $10^{12}$ organisms per milliliter. The small intestine, by contrast, is designed to be relatively sterile, with bacterial counts rarely exceeding $10^3$ to $10^4$ organisms per milliliter.
When the Migrating Motor Complex (MMC)—the physiological “clearing wave” that sweeps food remnants and residual bacteria from the small intestine into the colon between meals—becomes impaired (frequently triggered by anti-vinculin antibodies following food poisoning), colonic bacteria backwash across the ileocecal valve into the small intestine.
| SIBO Clinical Variant | Dominant Microbial Gas Produced | Primary Microbial Culprit | Resulting IBS Phenotype |
|---|---|---|---|
| Hydrogen-Dominant SIBO | Hydrogen Gas (H₂) | Fermenting bacteria (E. coli, Klebsiella, Enterococcus) | IBS-D (Diarrhea): Hydrogen gas stimulates mucosal secretion and rapid transit. |
| Intestinal Methanogen Overgrowth (IMO) | Methane Gas (CH₄) | Archaea (Methanobrevibacter smithii) | IBS-C (Severe Constipation): Methane acts as a paralytic neurotoxin, slowing intestinal transit by >60%. |
| Hydrogen Sulfide SIBO | Hydrogen Sulfide (H₂S) | Sulfate-reducing bacteria (Desulfovibrio) | Visceral Pain & Diarrhea: Rotten-egg flatulence, severe bladder/gut burning pain. |
Diagnostic Gold Standard: SIBO is diagnosed via a non-invasive Lactulose or Glucose Breath Test (LBT). If breath hydrogen rises ≥ 20 ppm or methane reaches ≥ 10 ppm within 90 minutes, SIBO is confirmed. Eradicating the small intestinal overgrowth with targeted antimicrobial herbs (berberine, oregano oil, neem, allicin) or prescription rifaximin resolves IBS symptoms in up to 70% of cases.
4. The Monash University 3-Phase Low-FODMAP Protocol
Developed by clinical researchers at Monash University in Melbourne, Australia, the Low-FODMAP Diet is the most clinically validated dietary intervention for IBS, demonstrating significant symptom reduction in up to 76% of randomized controlled trial participants.
FODMAP is an acronym for Fermentable Oligosaccharides, Disaccharides, Monosaccharides, And Polyols. These short-chain carbohydrates are poorly absorbed in the human small intestine, triggering symptoms via two distinct biophysical mechanisms:
- Osmotic Fluid Load: Being small, osmotically active molecules, FODMAPs draw massive amounts of water into the small intestinal lumen, triggering abdominal distension and rapid, watery diarrhea.
- Rapid Microbial Fermentation: Upon arriving unabsorbed in the distal ileum and colon, resident bacteria rapidly ferment these sugars, producing voluminous clouds of hydrogen, carbon dioxide, and methane gas within minutes. In a patient with visceral hypersensitivity, this gas causes agonizing pain.
The Critical 3 Phases (Why Lifelong Elimination is Harmful)
A dangerous consumer misconception is that the Low-FODMAP diet is meant to be followed indefinitely. Because FODMAPs (particularly fructans and inulin) are vital prebiotics that feed beneficial colonic species like Bifidobacterium longum and Akkermansia, staying on strict elimination for more than 8 weeks induces profound colonic dysbiosis. The protocol must follow three structured phases:
- Phase 1: Elimination (2 to 6 weeks): Strictly swap high-FODMAP foods for low-FODMAP alternatives to achieve clinical symptom control.
- Phase 2: Reintroduction (6 to 8 weeks): Systematically test individual FODMAP subgroups one at a time over 3-day challenge periods to map specific molecular triggers.
- Phase 3: Personalization (Long-Term): Reintroduce tolerated FODMAP foods to maximize prebiotic dietary variety and protect colonocyte health.
5. Evidence-Based Botanicals & Therapeutics for IBS
In clinical trials, several natural compounds have demonstrated therapeutic efficacy matching or exceeding synthetic pharmaceutical antispasmodics:
1. Enteric-Coated Peppermint Oil (Mentha x piperita)
Endorsed by the American College of Gastroenterology, enteric-coated peppermint oil is one of the most rigorously validated natural antispasmodics in gastroenterology. In a landmark randomized, double-blind, placebo-controlled clinical trial published in Gastroenterology (PMID: 31404118), targeted small-intestinal release peppermint oil produced statistically significant reductions in abdominal pain, discomfort, and overall IBS symptom severity.
By preventing calcium influx into intestinal myocytes, L-menthol directly halts spasmodic smooth muscle contraction, relieving abdominal cramping, normalizing colonic transit, and reducing gas pressure. In a meta-analysis of 12 randomized clinical trials, peppermint oil demonstrated a remarkable Number Needed to Treat (NNT) of just 3 to 4.
The Mandatory Enteric Coating: Standard peppermint oil relaxes the lower esophageal sphincter if released in the stomach, precipitating severe acid reflux. Enteric-coated capsules resist gastric acid, dissolving exclusively in the alkaline pH of the distal small intestine where antispasmodic menthol is clinically required.
2. Partially Hydrolyzed Guar Gum (PHGG)
While traditional roughage (such as wheat bran or coarse psyllium) frequently worsens bloating and abdominal pain in IBS, Partially Hydrolyzed Guar Gum (PHGG) is a unique, non-gelling water-soluble prebiotic fiber. Produced by enzymatic cleavage of guar bean endosperm, PHGG is certified Low-FODMAP.
PHGG is fermented slowly along the entire length of the colon without producing sudden gas spikes. It acts as a bidirectional bowel regulator: softening hard stools in IBS-C while firming loose stools in IBS-D, all while selectively multiplying butyrate-producing Faecalibacterium prausnitzii populations.
3. Gastric-Resistant Spore-Forming Probiotics (Bacillus coagulans)
Traditional non-spore probiotic strains (such as generic Lactobacillus acidophilus) frequently fail in IBS because over 90% are killed by harsh gastric stomach acid and bile salts before reaching the ileum. In contrast, soil-based spore-forming organisms (like Bacillus coagulans MTCC 5856 and Bacillus subtilis) possess a natural protective endospore coat.
They survive 100% of gastric transit, germinating exclusively in the small and large intestines. Multiple double-blind placebo-controlled trials confirm that daily spore supplementation produces statistically significant reductions in visceral abdominal pain, gas volume, and postprandial urgency.
Recommended Clinical Gut Health Essentials
Laboratory-tested, Low-FODMAP certified therapeutics selected for IBS remission.
Heather’s Tummy Tamers Peppermint Oil Capsules
Features authentic enteric-coated softgels formulated with pure peppermint, fennel, and ginger oils to relieve cramping and intestinal spasms without causing acid reflux.
Tomorrow’s Nutrition Sunfiber (100% PHGG Powder)
Monash University Low-FODMAP Certified, non-gelling soluble fiber powder that dissolves clear without grit, regulating bowel regularity in both IBS-C and IBS-D.
Probiogen Daily Digestive Spore Probiotic
Smart Spore technology delivering resilient Bacillus coagulans and subtilis that survive 100% of stomach acid to soothe visceral sensitivity and restore colonic balance.
Related Clinical & Digestive Guides
- Microbiome Barrier Defense: The Complexity of the Gut: Microbiome, Mucosal Immunity & Digestion
- Constipation Management: Natural Remedies for Constipation: 7 Clinically Proven Ways to Restore Regularity
- Hepatic Clearance & Motility: Liver Health Essentials: Phase I & II Detox Science, Silymarin & Protocols
- Gut-Brain Mental Health: Calm Your Mind: Natural Remedies for Anxiety, Stress & Nervous System Balance
- Fermentation Science & Flora: How to Make Probiotic Lemonade: Wild Fermentation Science & Gut Flora
Frequently Asked Questions (FAQ)
Is IBS a lifelong, incurable condition?
No. While historically labeled lifelong, identifying and resolving underlying root causes—such as SIBO, post-infectious dysbiosis, or specific FODMAP triggers—enables many patients to achieve complete clinical remission.
Why does regular peppermint tea make my heartburn worse?
Liquid peppermint tea releases menthol in the upper esophagus and stomach, relaxing the lower esophageal sphincter (LES) and precipitating acid reflux. Enteric capsules prevent this by dissolving only in the small intestine.
How do you differentiate between IBS and Inflammatory Bowel Disease (IBD)?
IBS is a functional disorder of gut-brain interaction without macroscopic tissue destruction. In contrast, IBD (Crohn’s or Ulcerative Colitis) causes structural mucosal ulcerations and marked elevations in fecal calprotectin.
Final Medical Takeaway
Living with Irritable Bowel Syndrome is not a psychological failing, nor is it something you must passively endure. By recognizing the true biological realities of visceral hypersensitivity and the gut-brain axis, screening for underlying SIBO bacterial fermentation, utilizing the structured Low-FODMAP reintroduction protocol, and soothing intestinal spasms with enteric-coated peppermint oil and gentle PHGG prebiotic fiber, you can reclaim predictable digestive comfort and vitality from the inside out.