
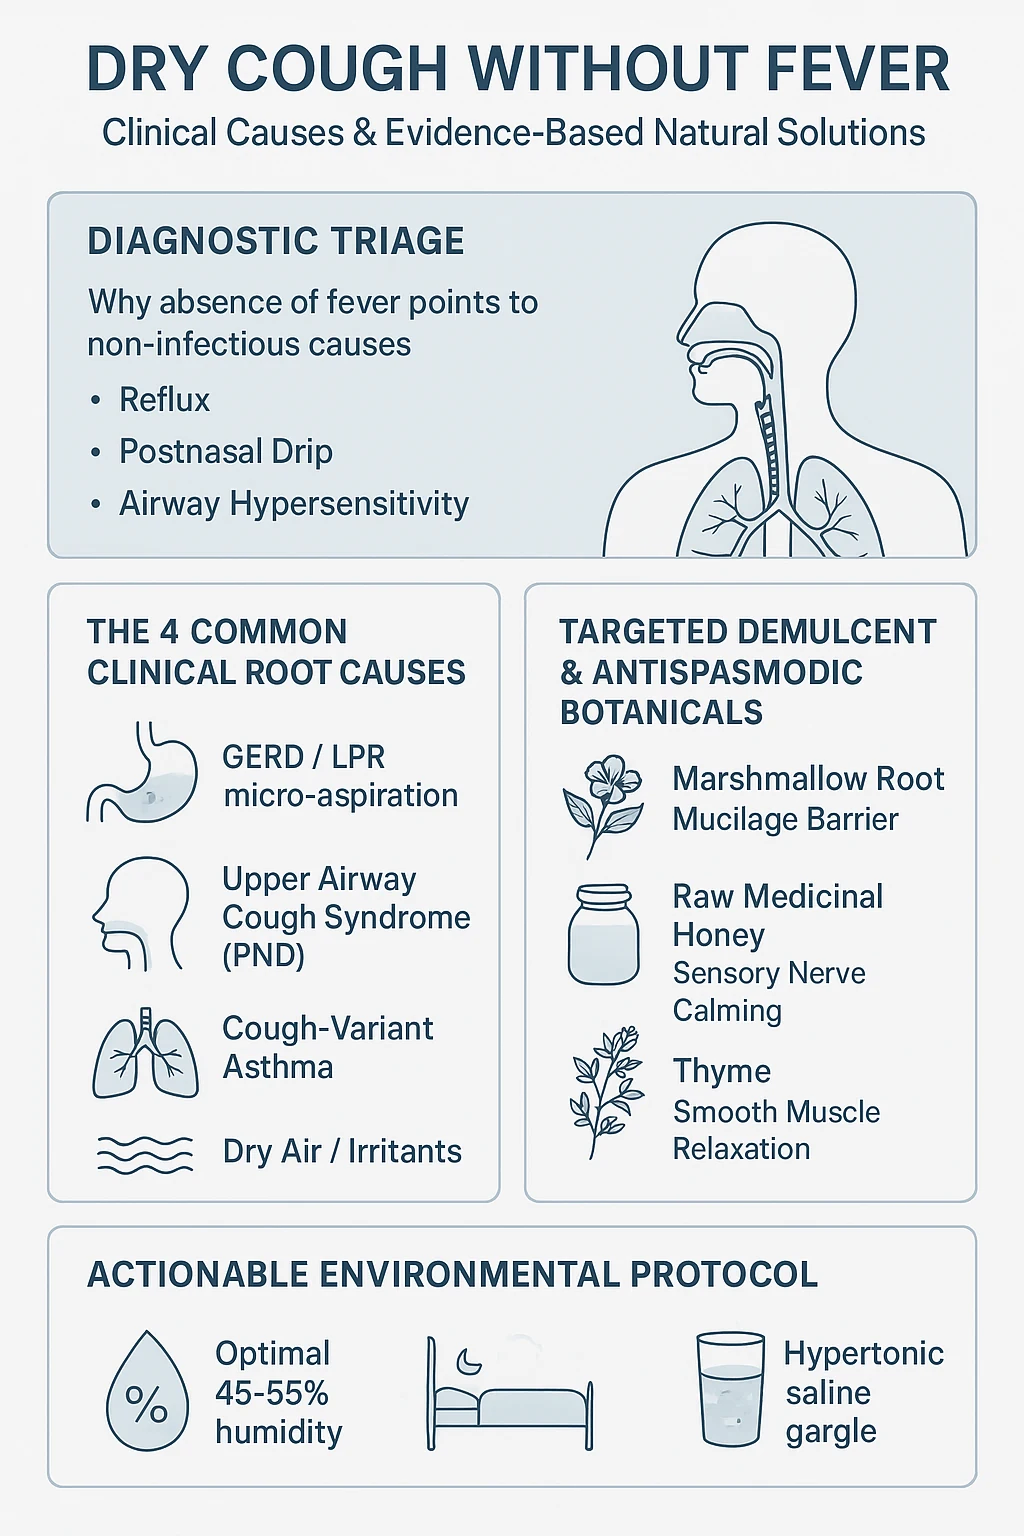
Quick Medical Summary: A persistent dry cough in the complete absence of a fever indicates non-infectious, anatomical, chemical, or neurogenic irritation rather than active bacterial pneumonia or acute viral influenza. The primary underlying etiologies include Upper Airway Cough Syndrome (postnasal drip), Gastroesophageal Reflux Disease (silent reflux/LPR), Cough-Variant Asthma (CVA), post-viral sensory vagal neuropathy, and ACE inhibitor antihypertensive medications. While over-the-counter suppressants carry sedation risks, targeted botanical demulcents (such as cold-macerated marshmallow root and high-potency raw honey) coat hypersensitive vagal C-fibers and desensitize airway receptors. Seek immediate emergency care for hemoptysis (coughing blood), resting dyspnea, or sudden stridor.
1. The Neurobiology of the Cough Reflex Arc: Why Does It Tickle?
An afebrile dry cough is one of the most common yet frustrating symptoms evaluated in pulmonary medicine. Unlike a productive cough that clears purulent phlegm, an afebrile dry cough is a relentless, tickling hack. The lack of fever confirms that the cough is not driven by an invasive infection; instead, it indicates localized mucosal irritation or heightened neurogenic sensitivity.
Understanding why an afebrile cough persists requires examining the sensory architecture of the airway tree:
- Afferent Vagal Sensors: The epithelial lining of the pharynx, larynx, vocal cords, and trachea is densely innervated by branching sensory fibers of the vagus nerve (Cranial Nerve X). These comprise mechanoreceptors (responding to physical mucus dripping) and unmyelinated C-fibers expressing TRPV1 and TRPA1 ion channels, which fire upon chemical, acidic, or thermal shifts.
- The Medullary Processing Relay: Signals travel to the nucleus tractus solitarius (NTS) in the brainstem, which regulates the cough threshold.
- The Motor Cascade: When triggered, efferent signals close the glottis while expiratory abdominal muscles contract, generating intrathoracic pressures over 300 mmHg before air expels at hundreds of miles per hour.
According to the official CHEST Clinical Practice Guidelines on Neurogenic Cough and Cough Hypersensitivity (PMID: 32061928), repeated mechanical coughing in the absence of secretions denudes the epithelial barrier. This perpetuates Cough Hypersensitivity Syndrome (CHS), where even cool ambient air triggers violent coughing fits. For productive vs non-productive distinctions, consult our overview of natural remedies for cough.
2. The 6 Primary Causes of Dry Cough Without Fever
When an active systemic infection is excluded, evidence-based clinical diagnostics evaluate six primary physiological mechanisms:
1. Upper Airway Cough Syndrome (UACS) & Postnasal Drip
UACS accounts for 30% to 40% of all chronic afebrile coughs. Driven by seasonal allergic rhinitis, perennial dust sensitivities, or vasomotor rhinitis, hyper-viscous secretions trickle down the posterior pharynx, stimulating mechanical cough receptors. Hallmarks include frequent throat-clearing, a sensation of mucus pooling in the pharynx, and worsening cough when lying flat. Reviewing the true cause of allergies provides deeper insight into histamine management.
2. Gastroesophageal Reflux Disease (GERD) & Silent LPR
Reflux is the second most common trigger, frequently manifesting with zero heartburn—a condition known as Laryngopharyngeal Reflux (LPR) or “silent reflux.” Aerosolized gastric hydrochloric acid and the digestive enzyme pepsin travel past the upper esophageal sphincter to irritate vocal cords and laryngeal tissue. Additionally, acid contacting the distal esophagus triggers the esophagobronchial reflex, eliciting bronchospasms via shared vagal innervation.
3. Cough-Variant Asthma (CVA)
Unlike classic asthma marked by wheezing and severe dyspnea, Cough-Variant Asthma presents exclusively with a persistent dry cough. It involves mild eosinophilic tracheobronchial inflammation that induces hyperresponsiveness to cold dry air, aerobic exertion, or laugh triggers. For holistic management strategies, explore our guide to asthma management and respiratory support.
4. Post-Viral Airway Hyperreactivity (Subacute Cough)
Following a common cold or influenza, fever and active pathogens disappear, yet an agonizing dry hack can persist for 3 to 8 weeks. Initial viral inflammation causes extensive epithelial denudation, exposing bare sensory C-fibers and upregulating TRPV1 receptors. To speed early viral clearance in future illnesses, see our evidence-based guide on natural treatments for colds and flu.
5. Medication-Induced Cough: ACE Inhibitors
Prescription ACE inhibitors (such as lisinopril, enalapril, and ramipril) inhibit the breakdown of bradykinin and substance P in pulmonary tissue. In up to 20% of patients, this causes intense mucosal hypersensitivity and a chronic tickling cough resistant to all syrups. The only definitive cure is physician-guided transition to an Angiotensin Receptor Blocker (ARB).
6. Environmental Dry Air & Volatile Organic Compounds (VOCs)
Indoor ambient humidity below 30% dries out the respiratory epithelial lining fluid, concentrating airway osmolarity and triggering osmotic cough receptors. Similarly, synthetic room fragrances, aerosol sprays, and off-gassing chemicals directly activate bronchial TRPA1 irritant receptors.
3. Targeted Botanical Protocols for Dry Cough Relief
Conventional over-the-counter suppressants carry sedation and rebound risks. In contrast, clinically validated botanical demulcents coat bare nerve endings, interrupt hypersensitive afferent signaling, and restore mucosal moisture balance:
- Cold-Macerated Marshmallow Root (Althaea officinalis): Rich in high-molecular-weight rhamnogalacturonan polysaccharides, marshmallow root forms a slick hydrocolloidal matrix over stripped pharyngeal mucosa. These complex branched polymers adhere electrostatically to mucosal epithelial membranes, shielding exposed vagal C-fibers from turbulent air friction and gastric acid micro-droplets. Preparation rule: Macerate 2 tablespoons of dried root in cold or room-temperature filtered water for 4 to 8 hours; never boil, as excessive heat denatures delicate mucilage polymers into inert simple sugars. Sip the viscous liquid slowly throughout the day.
- Certified Raw Manuka Honey: Provides high physical viscosity, enzymatic glucose oxidase activity (which generates gentle antimicrobial hydrogen peroxide), and concentrated methylglyoxal (MGO) bioactivity. In a comprehensive Cochrane systematic review (PubMed PMID: 30514138), researchers analyzed multiple randomized controlled trials and confirmed that honey was significantly more effective than placebo or diphenhydramine at reducing cough frequency, severity, and sleep disruption. Taking 1 to 2 teaspoons slowly from a spoon 30 minutes before sleep coats irritated sensory afferents and calms paroxysmal nighttime coughing spasms. (Critical Safety Rule: Contraindicated in infants <12 months due to infant botulism risk from dormant environmental spores).
- Slippery Elm Bark (Ulmus rubra): Especially effective when cough is triggered by laryngopharyngeal acid reflux. Its rich mucilaginous content coats the esophagus and hypopharynx, providing a durable physical barrier that neutralizes micro-aerosolized pepsin and hydrochloric acid before they damage vocal cord mucosa.
- Ultrasonic Bedroom Humidification: Maintaining indoor relative humidity between 45% and 55% prevents nocturnal airway desiccation and preserves the ciliary beat frequency of the respiratory tree. Always fill humidifiers with distilled or reverse-osmosis water to avoid aerosolizing mineral dust and sanitize tanks twice weekly.
4. Clinical Cause vs. Botanical Intervention Diagnostic Table
Use this diagnostic matrix to match specific symptoms with the most effective targeted botanical intervention:
| Suspected Etiology | Key Diagnostic Clues | Primary Mechanism | First-Line Natural Therapy | Optimal Protocol |
|---|---|---|---|---|
| Upper Airway Cough Syndrome | Frequent throat-clearing, cobblestone pharynx, supine worsening | Mechanoreceptor stimulation by postnasal drip | Marshmallow Root & Saline Sinus Rinse | Cold infusion sipped daily; nasal rinse BID |
| GERD & Silent Reflux (LPR) | Cough after meals, globus sensation, sour morning taste | Pepsin & acid micro-aspiration onto vocal folds | Slippery Elm & Torso Wedge Elevation | Slurry before meals; 30-degree incline bed |
| Cough-Variant Asthma | Triggered by cold air, exertion; 3:00 AM nocturnal peaks | Eosinophilic airway hyperreactivity without wheeze | Thyme Infusion & Quercetin | 300 mg thyme extract + 500 mg quercetin BID |
| Post-Viral Hyperreactivity | Lingering 3–8 weeks post-cold; scratchy tickle on deep inhale | Denuded epithelium exposing sensory vagal C-fibers | Raw Manuka Honey & Demulcents | 1 tbsp raw honey at bedtime; herbal tea |
| ACE Inhibitor Cough | Onset after starting blood pressure pill; refractory tickle | Bradykinin & substance P accumulation in lungs | Physician Review (Switch to ARB) | Medication change required for full resolution |
| Dry Air / Low Humidity | Worse during winter heating; dry nasal passages, chapped lips | Epithelial fluid evaporation activating ion channels | Cool Mist Humidifier & Throat Coat Tea | Maintain 45%–55% indoor humidity continuously |
5. Clinician-Selected Respiratory & Throat Essentials
When choosing natural remedies for an afebrile dry cough, third-party laboratory verification, purity, and clinical potency are critical. Below are three premier clinician-vetted formulations:
Top Clinical-Grade Dry Cough Relief Essentials
Traditional Medicinals Organic Throat Coat Tea (16 Tea Bags)
Pharmacopoeial-grade herbal tea formulated with organic marshmallow root, slippery elm inner bark, and wild licorice root. Delivers an immediate soothing colloidal film over tickling pharyngeal nerves.
Manukora Raw Manuka Honey MGO 850+ / UMF 20+ (250g)
Ultra-pure monofloral New Zealand raw Manuka honey with exceptional methylglyoxal bioactivity. Provides thick hyperosmolar throat coating and clinical sensory nerve calming before bed.
LEVOIT Ultrasonic Cool Mist Bedroom Humidifier (Classic 300S)
Whisper-quiet smart ultrasonic humidifier with built-in digital humidistat that automatically maintains the therapeutic 45%–55% humidity sweet spot all night long, eliminating nocturnal dry air cough spasms.
FTC Compliance Notice: Herbs & Health participates in affiliate marketing programs. When you purchase through the verified Amazon links above, we may earn an affiliate commission at no additional cost to you. We only recommend products tested for botanical integrity and clinical safety.
6. Red Flag Symptoms: When to Seek Immediate Medical Evaluation
While an afebrile dry cough is predominantly benign, certain clinical warning signs demand urgent evaluation by a board-certified pulmonologist or otolaryngologist:
- Hemoptysis: Coughing up even trace amounts of bright red blood or rust-colored streaks.
- Unexplained Weight Loss: Significant involuntary weight loss occurring alongside persistent coughing.
- Dyspnea at Rest: Shortness of breath, air hunger, or audible inspiratory stridor.
- Persistent Hoarseness: Progressive voice changes lasting beyond 3 weeks, warranting direct vocal cord laryngoscopy.
- Orthopnea: Waking gasping for air and needing multiple pillows to sleep (suggestive of cardiac strain).
- Cough in Heavy Smokers: A cough of altered character lasting longer than 8 weeks in individuals over 50 with a tobacco history.
Related Clinical & Respiratory Guides
- Comprehensive Cough Relief: Natural Remedies for Cough: Evidence-Based Relief for Dry and Wet Coughs
- Viral Respiratory Care: What Are the Best Natural Treatments for Colds and Flu? Antiviral Science
- Chronic Airway Management: Asthma Management Guide: Symptoms, Triggers & Respiratory Support
- Histamine & Allergy Root Causes: The True Cause of Allergies: Immune Dysfunction & Histamine Overload
- Seasonal Hay Fever Solutions: Breathe Easy: Natural Remedies for Seasonal Allergies & Hay Fever
Frequently Asked Questions (Clinical FAQ)
Why is my dry cough drastically worse when I lie down in bed?
Supine posture removes gravitational resistance, allowing postnasal secretions to pool directly over posterior pharyngeal nerves. Additionally, lying flat facilitates silent gastric reflux of acid and pepsin into the hypopharynx. Sleeping on a gradual 30-degree torso wedge pillow counteracts both phenomena effectively.
Can drinking cold ice water trigger a dry coughing fit?
Yes. In post-viral hyperreactivity, airway sensory C-fibers express cold-activated TRPM8 and TRPA1 receptors. Sudden temperature drops from iced liquids provoke localized vasoconstriction and reflex bronchospasms. Lukewarm herbal infusions are significantly better tolerated.
How long does a post-viral dry cough typically last?
A post-viral cough lingering between 3 and 8 weeks is classified as subacute. It represents the physiological duration needed for denuded airway epithelium to regenerate. Coughs extending beyond 8 weeks require evaluation for asthma, GERD, or non-allergic rhinitis.
Will antibiotics cure my dry cough if I do not have a fever?
No. Antibiotics target bacterial infections, which present with fever, purulent sputum, and systemic inflammation. Prescribing antibiotics for an afebrile dry cough is ineffective, carries drug risks, and disrupts beneficial gut and oral microbiomes.
How do I tell if my cough is caused by blood pressure medication?
If you take an ACE inhibitor (such as lisinopril or enalapril), suspect drug etiology. The cough presents as an unyielding, dry, lower throat tickle that fails to respond to syrups. Resolving the cough requires physician-supervised discontinuation and transition to an ARB.