
Among the thirteen essential human vitamins, Vitamin B12 (cobalamin) holds a unique place in human biochemistry. It is the largest, most structurally intricate, and only vitamin containing a coordinated metallic trace element: a central cobalt ion (Co³⁺) suspended within a tetrapyrrole corrin macrocycle. Structurally akin to the iron-bearing heme ring in human hemoglobin, cobalamin serves as an irreplaceable catalytic cofactor in two fundamental, life-sustaining biochemical reactions: the epigenetic methylation of DNA and the mitochondrial generation of cellular ATP.
Despite its critical biological role, Vitamin B12 deficiency is among the most underdiagnosed metabolic disorders worldwide. Conventional serum testing frequently masks cellular-level depletion, allowing insidious neurological, cardiovascular, and hematological damage to progress unnoticed for years. Below is an exhaustive, clinical investigation into the four cobalamin forms, the multi-stage gastrointestinal absorption cascade, functional diagnostic biomarkers, and evidence-based repletion protocols.
Evidence-Based Clinical Summary
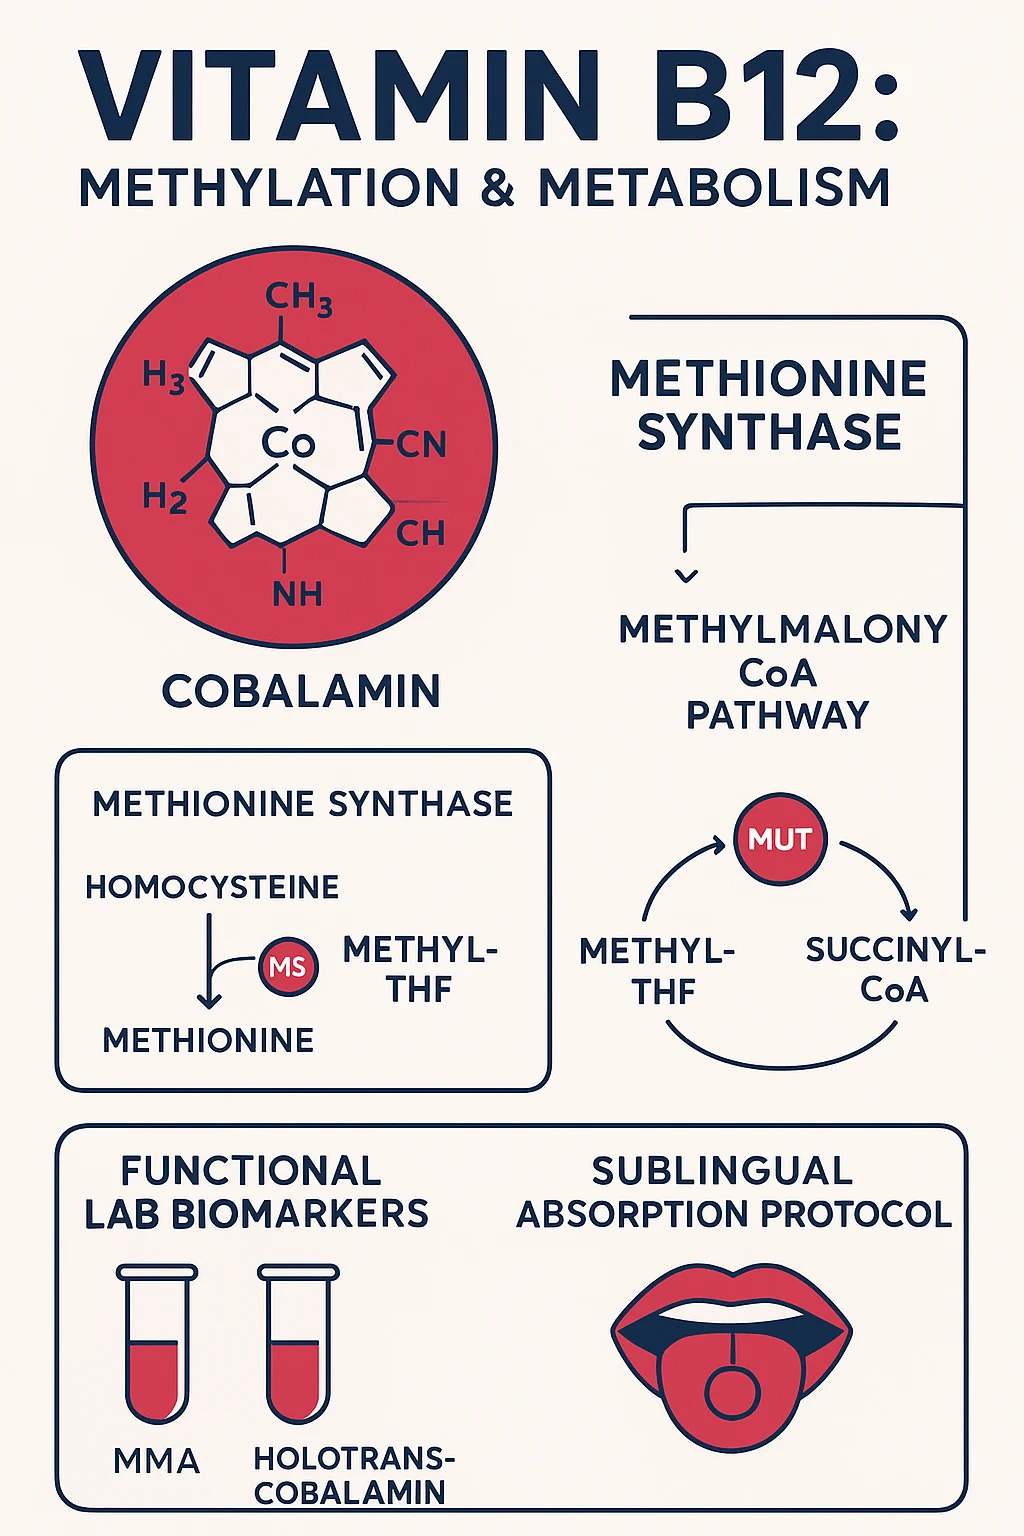
Vitamin B12 (cobalamin) is an organometallic coenzyme essential for genomic DNA methylation via cytoplasmic methionine synthase and myelin lipid stabilization via mitochondrial methylmalonyl-CoA mutase. Conventional serum tests frequently miss cellular deficiency in patients with “normal” levels between 200 and 450 pg/mL; definitive clinical evaluation requires measuring functional biomarkers: serum methylmalonic acid (MMA) and holotranscobalamin (HoloTC). For therapeutic repletion, high-dose sublingual coenzyme formulations (methylcobalamin and adenosylcobalamin) utilize 1–2% passive mucosal diffusion to achieve therapeutic blood levels even in patients lacking gastric intrinsic factor.
1. The Four Cobalamin Forms: Bioactive vs. Synthetic
In dietary supplements and clinical pharmaceuticals, cobalamin exists in four distinct molecular variations, distinguished by the upper axial ligand attached to the central cobalt atom. Understanding these chemical distinctions is critical for optimizing patient outcomes:
- Methylcobalamin (CH₃-Cbl): One of the two physiologically active coenzyme forms naturally utilized by human cells. As the primary cofactor for the cytoplasmic enzyme methionine synthase, methylcobalamin donates its methyl group directly to the methylation cycle, supporting homocysteine remethylation, neurotransmitter biosynthesis, and cellular detoxification without requiring metabolic conversion.
- Adenosylcobalamin (5′-deoxyadenosylcobalamin): The second naturally occurring bioactive coenzyme form, representing the dominant cobalamin fraction stored within human hepatic mitochondria and muscle tissue. It functions specifically as the obligate cofactor for mitochondrial methylmalonyl-CoA mutase, driving fatty acid metabolism and myelin lipid stabilization.
- Hydroxocobalamin (OH-Cbl): The predominant physiological form synthesized by commensal bacteria and found in unfortified animal foodstuffs. Hydroxocobalamin exhibits prolonged systemic circulation and superior cellular retention compared to synthetic forms. It also serves as an FDA-approved antidote for acute cyanide poisoning, binding cyanide ions to form benign cyanocobalamin excreted in urine.
- Cyanocobalamin (CN-Cbl): An entirely synthetic, non-physiological form produced by industrial fermentation and stabilized with a cyanide molecule. Although highly shelf-stable and cheap to manufacture, cyanocobalamin cannot be utilized directly by human enzymes. The liver must actively strip away the toxic cyanide moiety via decyanation, consuming intracellular reduced glutathione (GSH), before enzymatically methylating the remaining cobalamin. In smokers or individuals with compromised Phase II glutathione conjugation or renal impairment, cyanocobalamin accumulation can contribute to toxic cyanide accumulation and optic neuropathy (Leber’s hereditary optic neuropathy).
2. The Two Master Enzymatic Reactions Governed by B12
All human clinical manifestations of Vitamin B12 deficiency stem from the functional failure of just two enzymatic pathways:
Pathway 1: Cytoplasmic Methionine Synthase & The Methylation Cycle
Within the cellular cytoplasm, the enzyme methionine synthase (MTR) utilizes methylcobalamin to transfer a methyl group from 5-methyltetrahydrofolate (5-MTHF) to homocysteine, generating unmethylated tetrahydrofolate (THF) and L-methionine. Methionine is subsequently adenylated to form S-adenosylmethionine (SAMe), the universal methyl donor required for more than 200 cellular transmethylation reactions, including DNA methylation, histone modification, myelin basic protein synthesis, and the production of phosphatidylcholine, carnitine, creatine, dopamine, and melatonin.
When methylcobalamin is depleted, two immediate pathological consequences emerge:
- Hyperhomocysteinemia: Homocysteine accumulates rapidly in the vascular compartment, inducing endothelial oxidative stress, degrading elastin fibers, and activating prothrombotic coagulation cascades. In a seminal clinical trial published in the American Journal of Clinical Nutrition (PubMed PMID: 18703886), elevated plasma total homocysteine paired with low-normal B12 was strongly associated with accelerated neurocognitive decline and cerebral atrophy, highlighting the necessity of maintaining optimal remethylation capacity.
- The “Folate Trap”: Without methylcobalamin to receive the methyl group from 5-MTHF, cellular folate becomes biochemically trapped in the 5-MTHF configuration. This deprives the cell of free tetrahydrofolate required for purine and thymidylate synthesis, impairing nuclear DNA replication in rapidly dividing hematopoietic bone marrow precursors and precipitating megaloblastic macrocytic anemia (characterized by elevated Mean Corpuscular Volume, MCV > 100 fL, and hypersegmented neutrophils).
Pathway 2: Mitochondrial Methylmalonyl-CoA Mutase & Myelin Integrity
Within the mitochondrial matrix, the enzyme methylmalonyl-CoA mutase (MUT) relies on adenosylcobalamin to catalyze the isomerization of L-methylmalonyl-CoA into succinyl-CoA, an essential intermediate that feeds directly into the tricarboxylic acid (Krebs) cycle for mitochondrial oxidative phosphorylation and heme synthesis.
When adenosylcobalamin is deficient, methylmalonyl-CoA cannot convert to succinyl-CoA and hydrolyzes into methylmalonic acid (MMA). Pathologically elevated MMA acts as an antimetabolite: it displaces normal malonyl-CoA in fatty acid biosynthesis, leading to the incorporation of aberrant, branched-chain odd-carbon fatty acids into the phospholipid bilayer of neuronal myelin sheaths.
This progressive demyelination manifests clinically as subacute combined degeneration of the spinal cord (SCD), involving the posterior and lateral columns. Patients experience symmetrical bilateral paresthesias (“pins and needles” in the hands and feet), sensory ataxia, loss of vibratory sensation and proprioception, hyperreflexia, and cognitive deterioration (“megaloblastic madness”), neurological damage that can become irreversible if not treated promptly, even in the complete absence of anemia.
3. The 5-Stage Gastrointestinal Absorption Complex
Unlike simple water-soluble vitamins that passively diffuse across intestinal enterocytes, Vitamin B12 requires a sophisticated, highly vulnerable physiological relay race spanning from the oral cavity to the terminal ileum:
- Salivary Haptocorrin Binding: Dietary cobalamin enters the mouth bound to animal food proteins. In the oral cavity and stomach, salivary glands secrete haptocorrin (R-binder protein), which travels alongside the bolus.
- Gastric Cleavage & Acid Hydrolysis: Within the gastric fundus, hydrochloric acid (HCl) and pepsinogen (activated to pepsin) cleave cobalamin from dietary food proteins. Because free cobalamin is acid-sensitive, it binds avidly to haptocorrin, which shields it from denaturing in the acidic gastric environment. Concurrently, gastric parietal cells secrete Intrinsic Factor (IF), which remains unbound in low-pH gastric juice.
- Duodenal Proteolysis: Upon exiting the pylorus into the alkaline duodenum (pH > 7.0), pancreatic proteases (trypsin and chymotrypsin) digest haptocorrin. This releases cobalamin, which immediately binds to Intrinsic Factor, forming a stable, enzyme-resistant IF-Cbl complex.
- Terminal Ileal Endocytosis: The IF-Cbl complex journeys intact through 20 feet of small intestine until reaching the terminal ileum. Here, specialized apical enterocyte brush-border receptors called Cubam (composed of cubilin and amnionless proteins) recognize the Intrinsic Factor component in a calcium-dependent process, triggering receptor-mediated endocytosis.
- Transcobalamin Transport: Inside the ileal enterocyte, lysosomes degrade Intrinsic Factor, and free cobalamin is exported across the basolateral membrane into mesenteric portal capillaries, where approximately 20% binds to Transcobalamin II (HoloTC) for immediate delivery to peripheral tissues and bone marrow, while the remaining 80% binds to Transcobalamin I/III for hepatic storage.
Why Gut Dysfunction Causes Widespread B12 Depletion
Because B12 absorption depends on every single link in this gastrointestinal chain, any physiological disruption results in severe malabsorption:
- Proton Pump Inhibitors (PPIs) & H2 Blockers: Chronic suppression of gastric acid (omeprazole, pantoprazole, famotidine) prevents pepsin from cleaving cobalamin from dietary proteins, causing protein-bound B12 malabsorption.
- Metformin Pharmacotherapy: Long-term metformin use for Type 2 diabetes alters calcium-dependent membrane binding of the Cubam receptor complex in the terminal ileum, reducing B12 absorption by 10% to 30% in up to 40% of patients.
- Pernicious Anemia (Autoimmune Atrophic Gastritis): Autoantibodies targeted against gastric parietal cells ($H⁺/K⁺$ ATPase pumps) or directly against Intrinsic Factor itself permanently eradicate endogenous IF production, rendering oral food cobalamin completely unabsorbable.
- Ileal Resection & Crohn’s Disease: Surgical removal or transmural inflammation of the terminal ileum eliminates the specific Cubam receptor sites where absorption physically occurs.
4. Diagnostic Laboratory Matrix: Moving Beyond Deceptive Serum Tests
The standard reference range for total serum Vitamin B12 in most commercial laboratories spans roughly 200 to 900 pg/mL (148 to 664 pmol/L). However, in a landmark clinical review published in the New England Journal of Medicine (PubMed PMID: 23301732), Dr. Sally Stabler documented that normal serum cobalamin levels do not rule out severe functional tissue deficiency. Up to 30% of patients with early neuropsychiatric manifestations show “normal” serum B12 between 200 and 450 pg/mL, making secondary functional testing essential.
Total serum assays measure all circulating cobalamin indiscriminately, including inactive cobalamin analogs and molecules bound to haptocorrin that cannot be absorbed by peripheral tissues. To obtain an accurate assessment, physicians must evaluate functional secondary biomarkers:
| Biomarker Tested | Clinical Specimen | Optimal Functional Target | Diagnostic Significance |
|---|---|---|---|
| Methylmalonic Acid (MMA) | Serum or Urine | < 0.28 µmol/L (Serum) < 2.0 mg/g Cr (Urine) | The Gold Standard Functional Biomarker. Directly reflects intracellular mitochondrial adenosylcobalamin deficiency. Highly sensitive and specific. |
| Holotranscobalamin (HoloTC) | Serum | > 50 pmol/L | Active B12. Measures the precise ~20% fraction bound to transcobalamin II available for cellular uptake. Earliest marker to drop during depletion. |
| Total Homocysteine (tHcy) | Fasting Plasma | 6.0 – 8.0 µmol/L | Reflects cytoplasmic methylcobalamin and folate remethylation status. Levels > 10 µmol/L indicate impaired vascular methylation. |
| Mean Corpuscular Volume (MCV) | Whole Blood (CBC) | 85 – 92 fL | Macrocytosis (MCV > 100 fL) indicates advanced megaloblastosis; however, concurrent iron deficiency can mask macrocytosis with a normal MCV. |
5. Evidence-Based Repletion Protocols: Sublingual Passive Diffusion vs. Injections
For patients with intrinsic factor deficiency, pernicious anemia, or ileal malabsorption, conventional dogma historically dictated lifelong monthly intramuscular (IM) cyanocobalamin injections. However, extensive pharmacokinetic studies have revealed an alternative physiological mechanism: passive transmucosal diffusion.
Approximately 1% to 2% of any high-dose oral or sublingual cobalamin dose is absorbed directly across the oral sublingual mucosa and intestinal paracellular tight junctions via passive diffusion, completely independent of gastric acid, intrinsic factor, or ileal Cubam receptors. Thus, a daily sublingual dose of 1,000 to 2,000 mcg of bioactive methylcobalamin and adenosylcobalamin delivers 10 to 40 mcg of bioactive cobalamin into systemic circulation, far exceeding the physiological daily requirement of 2.4 mcg and matching the therapeutic efficacy of periodic intramuscular injections in randomized clinical trials.
The Methylation Synergy: B12 + Folate + B6
Repleting Vitamin B12 in isolation can uncover or exacerbate latent folate deficiencies. For optimal cellular methylation, B12 should be co-administered with active L-methylfolate (5-MTHF) and Pyridoxal-5-Phosphate (P-5-P, active Vitamin B6), particularly in individuals harboring common MTHFR (C677T/A1298C) or MTRR genetic polymorphisms who cannot efficiently metabolize synthetic folic acid.
Recommended Bioactive B12 Supplements
Clinically formulated sublingual coenzymes selected for maximum bioavailability.
Jarrow Formulas Methyl B-12 & Methyl Folate with P-5-P
Delivers 1,000 mcg Methylcobalamin, 400 mcg Quatrefolic (5-MTHF), and active B6 in quick-dissolve chewable lozenges for direct mucosal absorption.
Pure Encapsulations Adenosyl/Hydroxy B12 Liquid
Hypoallergenic liquid combining mitochondrial Adenosylcobalamin and prolonged-retention Hydroxocobalamin, ideal for sensitive individuals who tolerate unmethylated forms best.
MaryRuth Organics Vitamin B12 Liquid Drops (Methyl + Adenosyl)
Certified USDA Organic, vegan, and non-GMO liquid drops delivering both bioactive coenzyme forms for maximum cellular and neurological support.
Related Clinical Hematology & Recovery Guides
- Boosting Iron Naturally: Synergistic Remedies for Anemia, Hemoglobin & Fatigue
- C-Section Recovery Guide: 8 Evidence-Based Tips for Tissue Repair & Vitality
- Garlic & Brain Health: Neuroprotective Science, Apoptosis & Cellular Longevity
- Oncology Skin Recovery: Clinical Protocols for Epithelial & Barrier Healing
- Ashwagandha Safety Guide: Thyroid, Medication Interactions & Risk Profiles
Frequently Asked Questions (FAQ)
Can you overdose on Vitamin B12?
No. Vitamin B12 exhibits an exceptionally high safety profile with no established Upper Tolerable Intake Level (UL) set by the Institute of Medicine or European Food Safety Authority. Because it is water-soluble, any excess cobalamin beyond cellular saturation and hepatic storage capacity is excreted harmlessly via urine (often giving urine a slight pinkish-orange tint). Massive oral doses of 5,000 mcg daily have been administered in clinical trials for years without adverse toxicological effects.
Can high doses of folic acid mask a Vitamin B12 deficiency?
Yes, and this represents a dangerous clinical pitfall. High doses of synthetic folic acid (> 1,000 mcg daily) can bypass the “folate trap,” providing sufficient nucleotide intermediates to correct megaloblastic anemia and normalize hemoglobin levels. However, folic acid does not correct adenosylcobalamin deficiency in the mitochondria. As a result, methylmalonic acid continues to accumulate, allowing irreversible neurological demyelination of the spinal cord (subacute combined degeneration) to progress silently while blood counts appear deceptively healthy.
Can plant foods provide active Vitamin B12?
No. Authentic, biologically active cobalamin is synthesized exclusively by bacteria and archaea; plants do not synthesize or require it. While fermented soy (tempeh), spirulina, and nori algae are frequently marketed as plant B12 sources, analytical testing confirms they contain predominantly pseudo-vitamin B12 (inactive corrinoid analogs). These analogs can bind to human transcobalamin receptors without exhibiting enzymatic activity, paradoxically blocking the uptake of true cobalamin. Individuals on strict vegetarian or vegan diets must supplement with reliable oral methylcobalamin or adenosylcobalamin.
Final Clinical Takeaway
Vitamin B12 is an indispensable guardian of genomic stability, cardiovascular integrity, and neurological health. By choosing bioactive coenzymes over synthetic cyanocobalamin and utilizing functional MMA testing, you ensure optimal methylation and cellular resilience.