

Quick Medical Summary: Autism Spectrum Disorder (ASD) is a lifelong neurodevelopmental condition characterized by persistent differences in social communication, reciprocal social interaction, and restricted, repetitive patterns of behavior or intense interests (DSM-5-TR criteria). Rather than a single disease entity, autism reflects complex neurodevelopmental diversity involving altered postnatal synaptic pruning, an imbalance between excitatory glutamate and inhibitory GABAergic neurotransmission, and sensory processing differences. Emerging research highlights the profound role of the gut-brain axis, intestinal microbiome dysbiosis, and oxidative stress. Evidence-based support emphasizes early developmental screening (M-CHAT-R/F), occupational sensory integration, speech therapy, and targeted nutritional strategies including omega-3 fatty acids, targeted probiotics, and deep touch pressure modalities.
Understanding Autism Spectrum Disorder: The Modern Neurodevelopmental Paradigm
In clinical medicine and developmental psychology, our understanding of Autism Spectrum Disorder (ASD) has undergone a profound evolution. Historically divided into separate categories like Asperger’s Syndrome and PDD-NOS, the DSM-5 unified these under a dimensional spectrum model.
Crucially, the autism spectrum is not a linear continuum running from “mild” to “severe.” Rather, developmental pediatricians conceptualize ASD as a multidimensional wheel encompassing distinct functional domains: verbal and non-verbal communication, social reciprocity, sensory processing, executive functioning, and motor coordination. An individual may possess exceptional intellectual gifts and verbal fluency while experiencing debilitating sensory overload and executive dysfunction.
The DSM-5-TR establishes two core diagnostic dyads:
- Persistent Deficits in Social Communication & Interaction: Challenges in social-emotional reciprocity (e.g., initiating conversation, sharing emotions), nonverbal communicative behaviors (e.g., eye gaze modulation, reading body language), and developing, maintaining, and understanding peer relationships.
- Restricted, Repetitive Patterns of Behavior, Interests, or Activities: Stereotyped motor movements (hand flapping, spinning), rigid adherence to nonfunctional routines, intense fixated interests, and hyper- or hypo-reactivity to sensory input (e.g., adverse reactions to specific textures, sounds, or visual patterns).
Diagnostic criteria categorize support needs into three functional tiers: Level 1 (“Requiring Support”), Level 2 (“Requiring Substantial Support”), and Level 3 (“Requiring Very Substantial Support”). Epidemiological data published by the CDC Autism and Developmental Disabilities Monitoring (ADDM) Network (PubMed) confirms that proactive developmental screening and tailored accommodations significantly improve lifelong adaptive outcomes.
The Neurobiology of ASD: Synaptic Pruning, GABA & Connectivity
Extensive neuroimaging, post-mortem neuropathology, and molecular genetics demonstrate that autism is rooted in distinct neurodevelopmental architecture:
1. Altered Postnatal Synaptic Pruning: In typical early brain development, neurons initially form an excess of synaptic connections. During toddlerhood and childhood, the brain undergoes selective synaptic pruning—eliminating redundant or inefficient synapses to optimize neural processing. In autistic individuals, hyperactivation of the mTOR (mammalian target of rapamycin) signaling pathway inhibits normal autophagy, resulting in a persistent overabundance of dendritic spines. This causes “hyper-local” neural connectivity, where local circuits are intensely active but long-range communication between cerebral hemispheres is less integrated.
2. Excitation/Inhibition (E/I) Neurochemical Imbalance: A dominant neurobiological model of ASD is the dysregulation between excitatory glutamate and inhibitory GABA (gamma-aminobutyric acid) neurotransmission. Genetic variations frequently downregulate parvalbumin-positive GABAergic interneurons. Deprived of sufficient inhibitory brake signals, sensory and cognitive cortices become hyper-excitable, leading to sensory overwhelm, sleep disruptions, and acute autonomic distress—a neurochemical state mirroring patterns analyzed in our clinical anxiety relief guide.
3. Neuronal Membrane Phospholipids: The rapid growth of neuronal dendrites and myelin sheaths depends heavily on long-chain polyunsaturated fatty acids, particularly docosahexaenoic acid (DHA) and eicosapentaenoic acid (EPA). Clinical trials indicate that many autistic individuals exhibit altered fatty acid metabolism and elevated cellular oxidative stress, highlighting the importance of bioavailable omega-3 support.
To support neuronal membrane fluidity, synaptic signaling, and early neurodevelopment, purified omega-3 DHA provides foundational nutritional support:
Nordic Naturals Children’s DHA (Pure Arctic Cod Liver Oil)
Crafted exclusively from 100% wild Arctic cod, this liquid formula delivers concentrated omega-3 DHA and naturally occurring vitamins A and D. Extensively studied in pediatric trials to support brain development, visual processing, and cellular membrane plasticity.
- Pure triglyceride form for optimal cellular bioavailability and uptake
- Third-party tested for environmental toxins, heavy metals, and PCBs
- Natural strawberry flavor easily mixed into smoothies, juices, or yogurt
The Gut-Brain Axis & Microbiome Dysbiosis in Autism
Between 40% and 80% of children with autism spectrum disorder experience chronic gastrointestinal disturbances, including persistent constipation, chronic diarrhea, abdominal pain, and gastroesophageal reflux. Landmark investigations published in Cell by Caltech researchers (PubMed PMID: 24315484) demonstrated that gastrointestinal disturbances in ASD are fundamentally linked to the microbiome-gut-brain axis and mucosal barrier permeability.
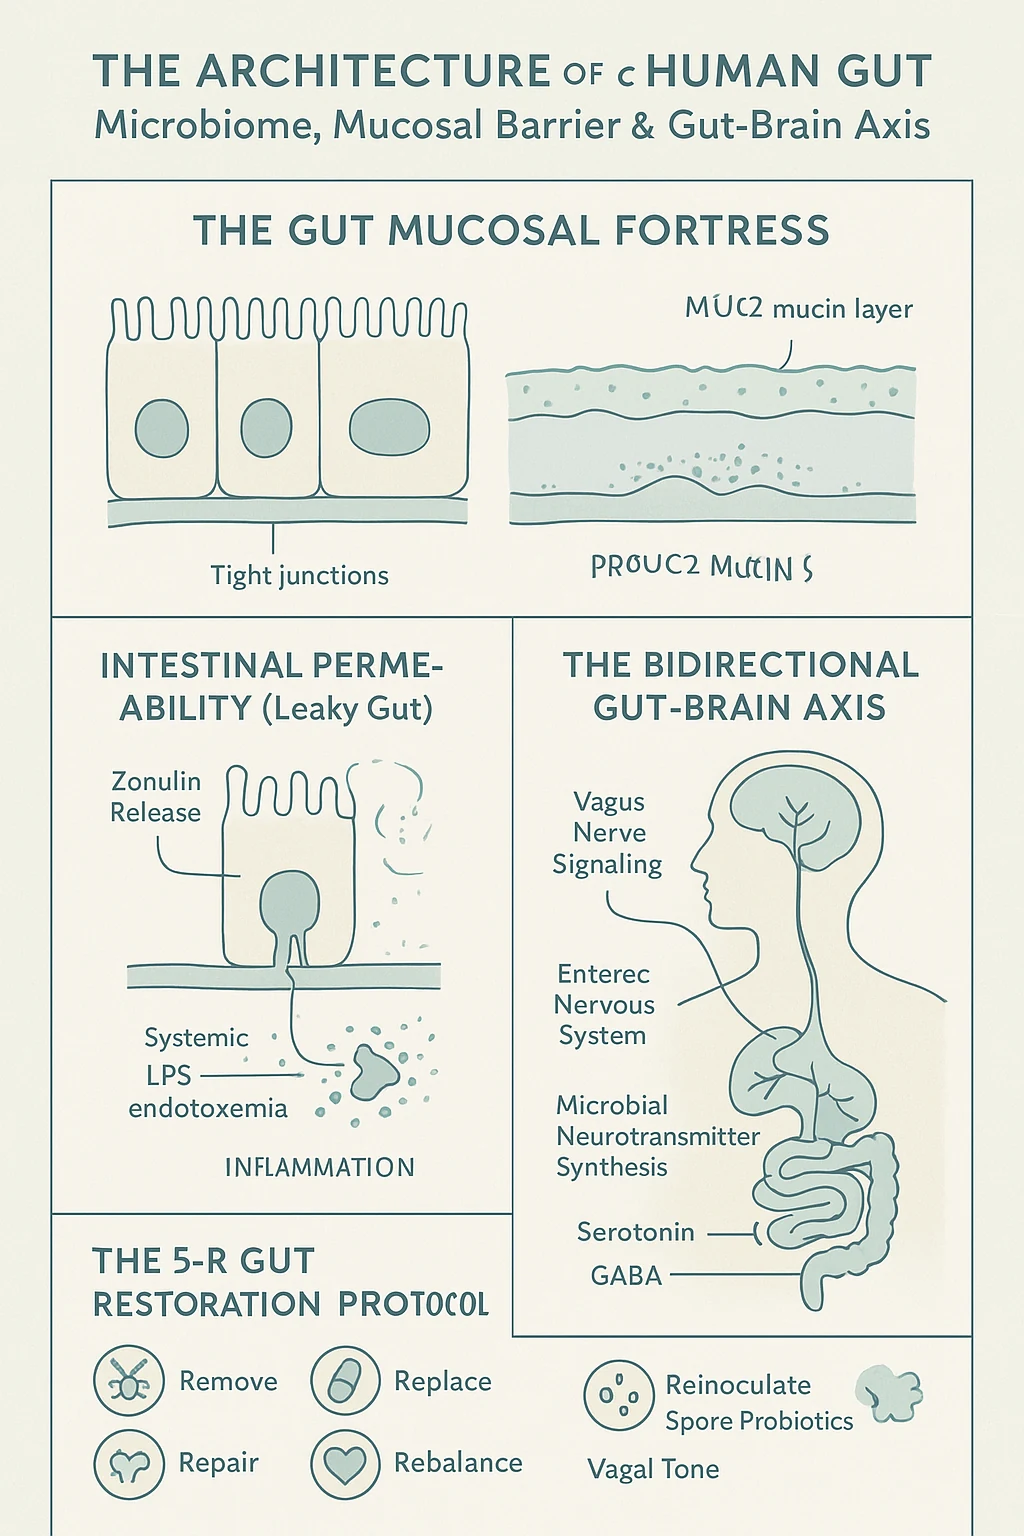
Metagenomic sequencing reveals that the fecal microbiome of autistic individuals frequently displays a lower abundance of beneficial commensal bacteria (such as Bifidobacterium and Lactobacillus) paired with an overgrowth of Clostridium species and reduced bacterial diversity. This dysbiosis alters the production of short-chain fatty acids (SCFAs). While moderate butyrate is neuroprotective, excessive propionic acid can cross the blood-brain barrier, triggering microglial activation and altering gene expression in neural pathways governing social behavior.
Furthermore, intestinal hyperpermeability (“leaky gut”) allows bacterial lipopolysaccharides (LPS) to enter systemic circulation, sparking low-grade systemic inflammation that exacerbates sensory sensitivities and behavioral distress. Clinical trials using targeted multi-strain probiotics and prebiotics show significant improvements in both GI comfort and core behavioral metrics.
To support intestinal barrier integrity, balance microbial fermentation, and soothe the gut-brain axis, clinical-grade diverse probiotics offer essential daily support:
Garden of Life Dr. Formulated Organic Kids Probiotics
Doctor-formulated organic chewable probiotic delivering 5 billion CFU across 14 diverse, acid-resistant strains, including beneficial Lactobacillus and Bifidobacterium species. Enhanced with organic whole-food prebiotic fiber to cultivate healthy gut flora and support digestive and immune balance.
- 14 diverse probiotic strains specifically selected for pediatric digestive and immune health
- Certified USDA Organic, Non-GMO Project Verified, gluten-free, and dairy-free
- Tasty chewable berry flavor with zero added sugar, artificial dyes, or fillers
Sensory Processing Differences & Deep Touch Pressure Therapy
Sensory processing atypicalities are central to the daily lived experience of autistic individuals. The nervous system may experience hyper-reactivity (sensory defensiveness, where fluorescent lighting or clothing seams cause physical distress), hypo-reactivity (high pain threshold, seeking intense movement), or a fluctuating combination across sensory modalities.
When sensory stimuli overwhelm neural processing capacity, the autonomic nervous system shifts into fight-or-flight hyperarousal, culminating in a sensory meltdown (an involuntary neurological overflow) or a shutdown (internal withdrawal and mutism). Conversely, stimming (self-stimulatory behaviors like rocking, flapping, or humming) is an adaptive regulatory mechanism that helps calm an overloaded nervous system or generate needed proprioceptive feedback.
One of the most effective, non-invasive occupational therapy interventions for sensory regulation is Deep Touch Pressure (DTP) therapy. Gentle, evenly distributed mechanical weight stimulates Ruffini endings and Pacinian corpuscles in the skin and fascia, increasing parasympathetic vagal tone. Clinical research confirms that DTP reduces sympathetic fight-or-flight signaling, blunts cortisol spikes, and stimulates serotonin and melatonin release, easing anxiety and facilitating restorative sleep.
For evidence-based sensory regulation, anxiety reduction, and improved sleep architecture, premium weighted blankets deliver gentle deep touch pressure therapy:
YnM Weighted Sensory Blanket (100% Oeko-Tex Cotton)
Constructed with smaller 4.7×4.7-inch compartments filled with micro-glass beads for perfectly uniform weight distribution. Applies calming deep touch pressure therapy across the body, helping soothe sensory overstimulation, reduce motor restlessness, and promote deeper sleep.
- Certified Oeko-Tex Standard 100 breathable, hypoallergenic natural cotton
- Evenly distributed glass beads provide comforting proprioceptive input without bulk
- Available in calibrated child and adult weights (recommended ~10% of body weight)
Developmental Screening & Diagnostic Pathways (M-CHAT to ADOS-2)
Early neurodevelopmental screening provides the critical window for neuroplastic intervention. The American Academy of Pediatrics (AAP) recommends universal autism screening for all children at 18 and 24 months of age using validated clinical tools such as the M-CHAT-R/F (Modified Checklist for Autism in Toddlers, Revised with Follow-Up).
Key developmental signs in early childhood include:
- Joint Attention Deficits: Not following a caregiver’s pointing finger or not pointing to show interest in an object by 14 to 18 months.
- Social Reciprocity Gaps: Inconsistent or absent response when their name is called, coupled with normal hearing; lack of shared smiles or warm facial expressions.
- Speech & Communication Milestones: Absence of single words by 15 to 18 months, lack of two-word meaningful phrases by 24 months, or any sudden loss or regression of previously acquired verbal or social skills at any age.
- Repetitive Object Use: Lining up toys in precise rows, spinning wheels continuously, or intense distress over minor environmental changes.
Formal clinical diagnosis is conducted by developmental pediatricians, child neurologists, or clinical psychologists using standardized assessment batteries: the Autism Diagnostic Observation Schedule, Second Edition (ADOS-2) and the Autism Diagnostic Interview-Revised (ADI-R).
The Female Autism Phenotype: Autistic girls and women are frequently underdiagnosed or identified late in adolescence or adulthood. Many exhibit strong social masking and camouflaging abilities, mimicking neurotypical peers at great metabolic cost, often presenting primarily with internalizing anxiety, sensory exhaustion, or atypical eating patterns.
Multidisciplinary Support Strategies: Therapy, Nutrition & Environment
Evidence-based autism support does not aim to “cure” neurodiversity, but rather to remove disabling environmental barriers, foster autonomous communication, and optimize physical health:
1. Speech and Occupational Therapy: Speech-Language Pathology (SLP) focuses on functional communication—including Augmentative and Alternative Communication (AAC) devices for non-speaking individuals. Occupational Therapy with Sensory Integration (OT/SI) helps individuals process vestibular, proprioceptive, and tactile input, fostering adaptive self-regulation.
2. Sensory-Friendly Environmental Accommodations: Tailoring physical spaces significantly reduces nervous system overload. Practical accommodations include dimmable warm lighting, noise-canceling headphones in loud environments, visual schedules to make daily transitions predictable, and designated quiet recovery zones.
3. Nutritional Triaging: Because sensory food aversions can restrict dietary intake to a narrow selection of “safe” foods, nutritional deficiencies (especially iron, zinc, magnesium, and vitamin D) are common. Pediatric blood panels should guide gentle supplementation rather than imposing rigid, unverified elimination diets that risk nutritional deficiencies.
Master Comparison Table: ASD Support Levels, Profiles & Accommodations
This clinical matrix summarizes the three DSM-5-TR support levels, characterizing communication profiles, behavioral patterns, and recommended environmental supports:
| Support Level | Social Communication Profile | Behavioral & Sensory Characteristics | Adaptive Daily Functioning | Recommended Clinical Supports |
|---|---|---|---|---|
| Level 1 (“Requiring Support”) | Speaks in full sentences; difficulty initiating social interactions; atypical peer rapport | Inflexibility causes interference in 1+ contexts; difficulty switching tasks; sensory sensitivities | Independent living achievable; struggles with executive functioning and organization | Speech pragmatics, OT sensory diet, visual organizers, neurodiversity-affirming coaching |
| Level 2 (“Requiring Substantial Support”) | Marked deficits in verbal/nonverbal communication; speaks simple sentences; limited reciprocity | Difficulty coping with change; repetitive behaviors appear frequently and are obvious to others | Requires daily support with complex tasks, financial management, or self-care routines | Intensive speech therapy, AAC devices, 1-on-1 school aide, structured sensory spaces |
| Level 3 (“Requiring Very Substantial Support”) | Few words of intelligible speech; rarely initiates interaction; responds only to direct cues | Extreme difficulty with change; repetitive behaviors severely interfere with all functional areas | Requires 24/7 continuous support for essential daily self-care and personal safety | Comprehensive multidisciplinary care, full-time caregiver support, robust AAC systems |
Related Clinical Guides & Neurodevelopmental Protocols
Explore complementary research-backed guides from our neurology and pediatric wellness library:
- Executive Functioning: Natural Remedies for ADHD: Nutrition, Nootropics & Focus Strategies
- Autonomic Regulation: Anxiety Relief Guide: HPA-Axis Balancing & Calming Botanicals
- Stress Neurobiology: Calm Your Mind: Natural Remedies for Anxiety & HPA Dysregulation
- Neural Connectivity: Daily Tea & Neuroprotection: NUS Brain Connectivity Findings
- Pediatric Gut Wellness: Natural Remedies for Kids with Nausea & Digestive Sensitivity
Frequently Asked Questions (FAQ)
What is the difference between a sensory meltdown and a behavioral tantrum?
A tantrum is goal-directed behavior intended to achieve a specific outcome; it subsides when the demand is met or an audience leaves. A sensory meltdown is an involuntary neurological overflow caused by overwhelming sensory input or cognitive exhaustion; it cannot be reasoned with and requires a quiet, safe, low-stimulation environment to resolve.
Can an individual be diagnosed with both ADHD and Autism?
Yes. The DSM-5 explicitly allows co-occurring diagnoses of ADHD and ASD. Studies indicate that 30% to 50% of autistic individuals also meet clinical diagnostic criteria for ADHD, sharing executive function and dopamine pathway differences explored in our guide to natural remedies and focus strategies for ADHD.
Is stimming harmful, and should it be stopped?
In the vast majority of cases, stimming (such as hand flapping, rocking, or vocalizing) is a healthy, natural self-regulatory mechanism that should never be suppressed. Intervention is only warranted if a stim is physically self-injurious, in which case occupational therapists redirect the behavior toward a safe sensory alternative.
Why are gastrointestinal problems so common in autistic children?
Autism is intimately connected to the gut-brain axis. Differences in enteric nervous system signaling, altered gut microbiome diversity, and autonomic tone frequently manifest as dysmotility and visceral hypersensitivity, often requiring gentle pediatric hydration protocols outlined in our review of natural remedies for childhood nausea and hydration.
Can adults be evaluated and diagnosed with autism?
Yes. Increasing numbers of adults seek late diagnosis after recognizing lifelong sensory sensitivities, social masking fatigue, or following a child’s diagnosis. Comprehensive adult neurodevelopmental evaluations review developmental childhood history alongside adult adaptive functioning to provide formal clinical validation.